
DIEP Flap Breast Reconstruction
Natural-tissue breast reconstruction using your own lower-abdominal skin and fat — no implant, and no sacrifice of the abdominal muscle.
The Deep Inferior Epigastric Perforator flap (DIEP flap) replaces the skin and soft tissue removed at mastectomy with tissue borrowed from the abdomen. A slim incision along the bikini line — much like a tummy tuck — is used to take the skin, soft tissue, and the small blood vessels needed for the reconstruction. Those vessels are matched to supplying vessels at the mastectomy site and reattached under a microscope.
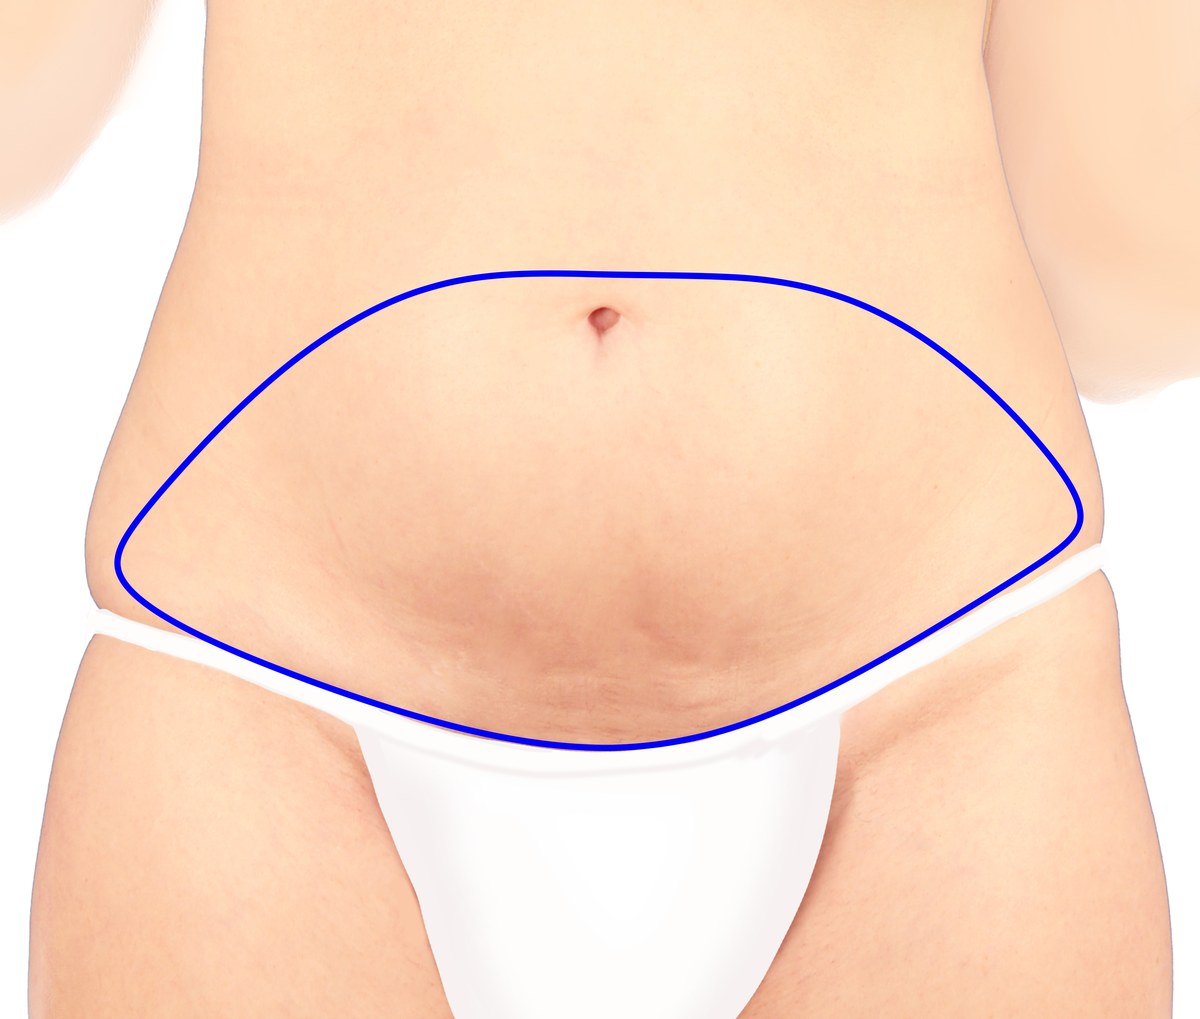
Unlike a conventional TRAM (Transverse Rectus Abdominis Muscle) reconstruction, the perforator technique collects the tissue without sacrificing the underlying abdominal muscles. The tissue is then shaped into a new breast mound. Because excess fat and skin are often found in the lower abdomen, the abdomen is a favorable donor site for many women — and the abdominal contour is often improved in the process, much like a tummy tuck.
SIEA Flap
In a select group of women, the vessels just beneath the skin (superficial inferior epigastric artery) can feed the abdominal tissue, allowing the surgeon to avoid the abdominal muscle entirely. Otherwise the procedure is the same as a DIEP, with the same low, tummy-tuck-like incision.
TRAM Flap
Similar in design, but in some cases a portion of the rectus muscle (one of the two vertical abdominal muscles) must be taken with the skin and fat, based on the patient’s anatomy. In Dr. Haddock’s practice this is rare — he can almost always use a DIEP or SIEA flap instead.
Why natural-tissue reconstruction
- It is permanent. The reconstruction is built from your own living tissue, so once it has healed it is simply part of you — there is nothing to exchange or replace later.
- It looks and feels natural. The reconstructed breast has the softness and movement of the tissue it is made from, and it typically blends into the chest rather than sitting on it.
- It is living tissue with its own blood supply. That means it stays at body temperature — it does not turn cold when the weather does, the way an implant can.
- It changes with you. Gain weight and the reconstruction gains with you; lose weight and it does the same. It follows your body over time instead of staying fixed.
- It stays fat — it never becomes breast tissue. The tissue that is moved is skin and fat, and it remains skin and fat, so it does not change your risk of breast cancer.
These advantages are shared by every natural-tissue reconstruction Dr. Haddock performs — DIEP, PAP, and LAP alike. Which donor site is right for you is a separate question, decided together after examination and imaging.
Before & After
Front views from seven of Dr. Haddock’s DIEP flap reconstructions — before on the left, after on the right.
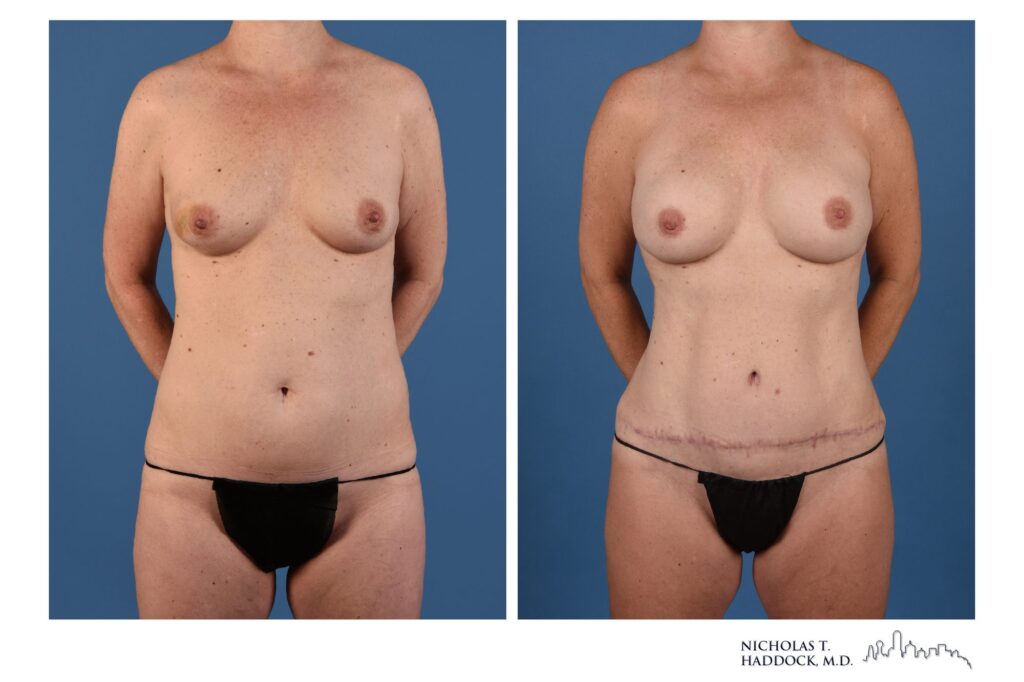
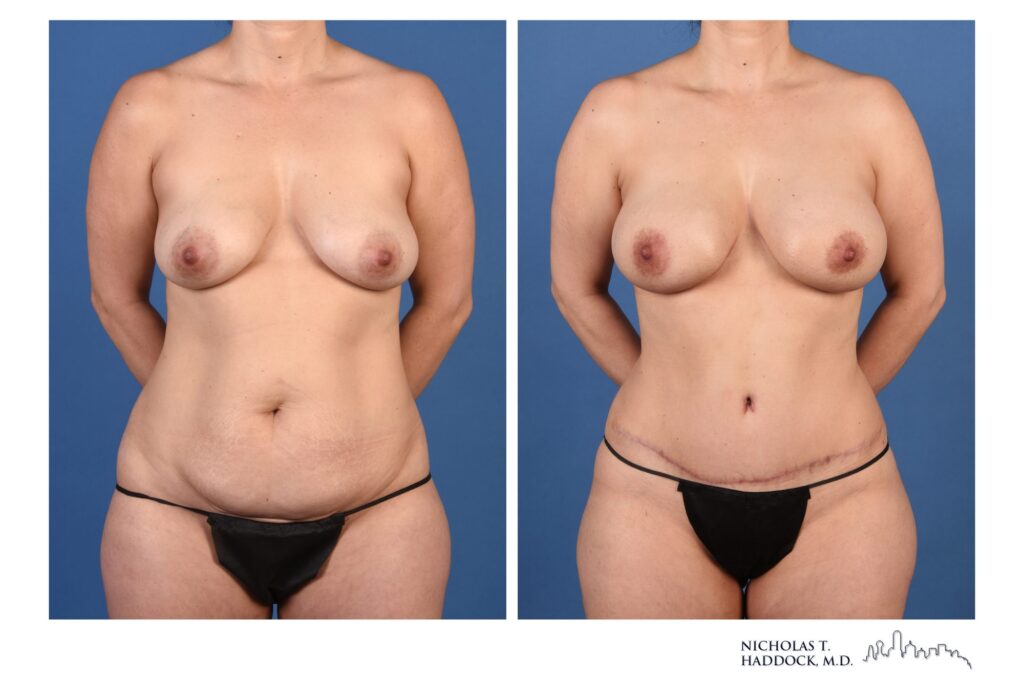
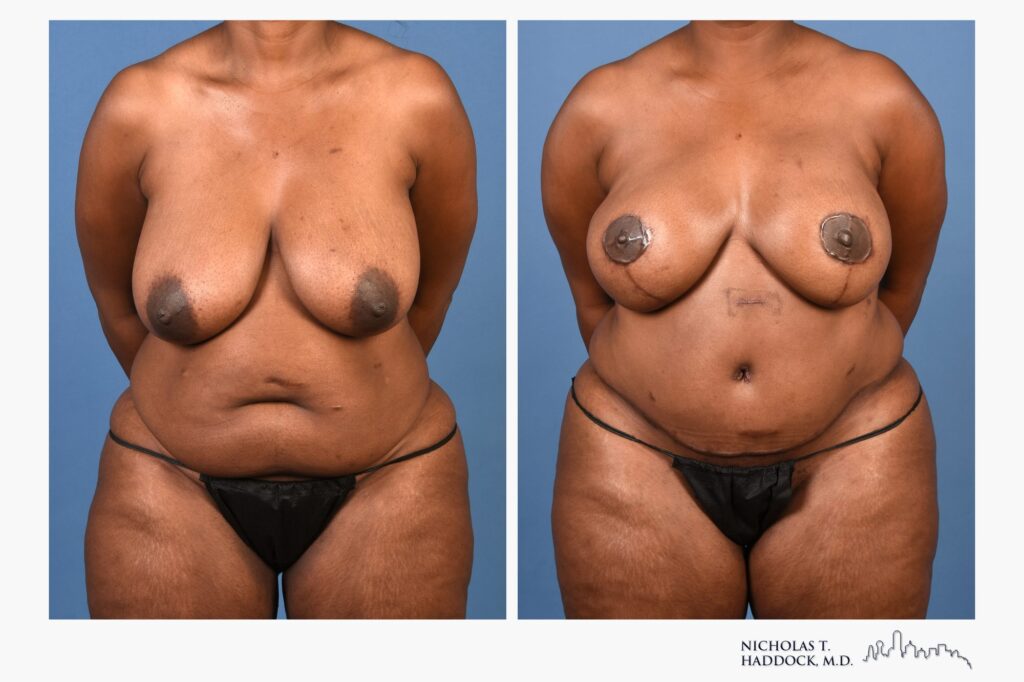
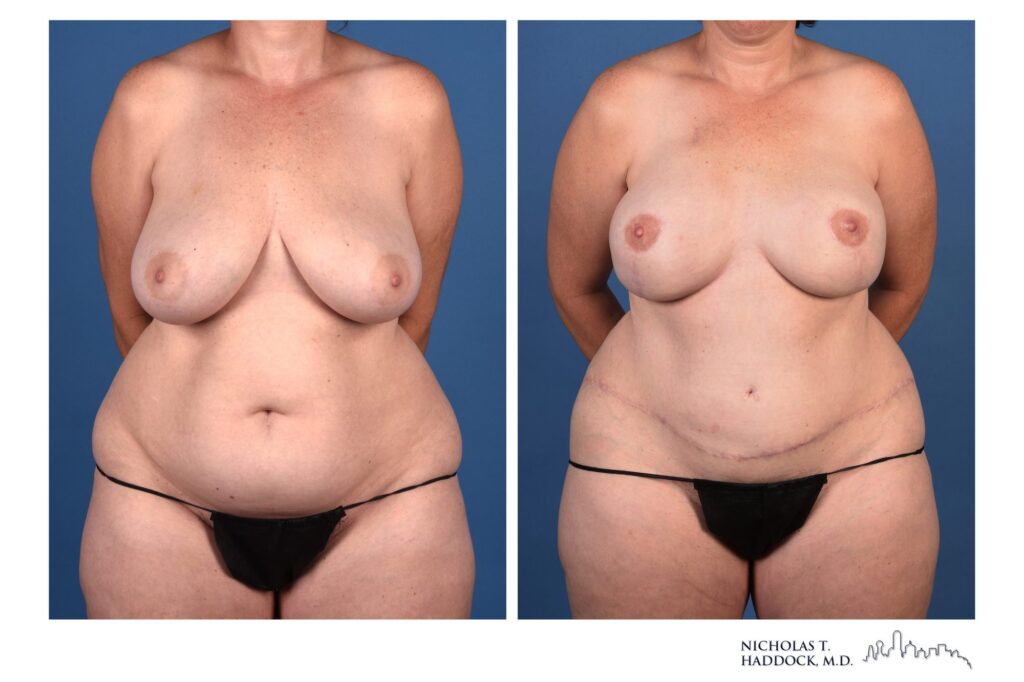
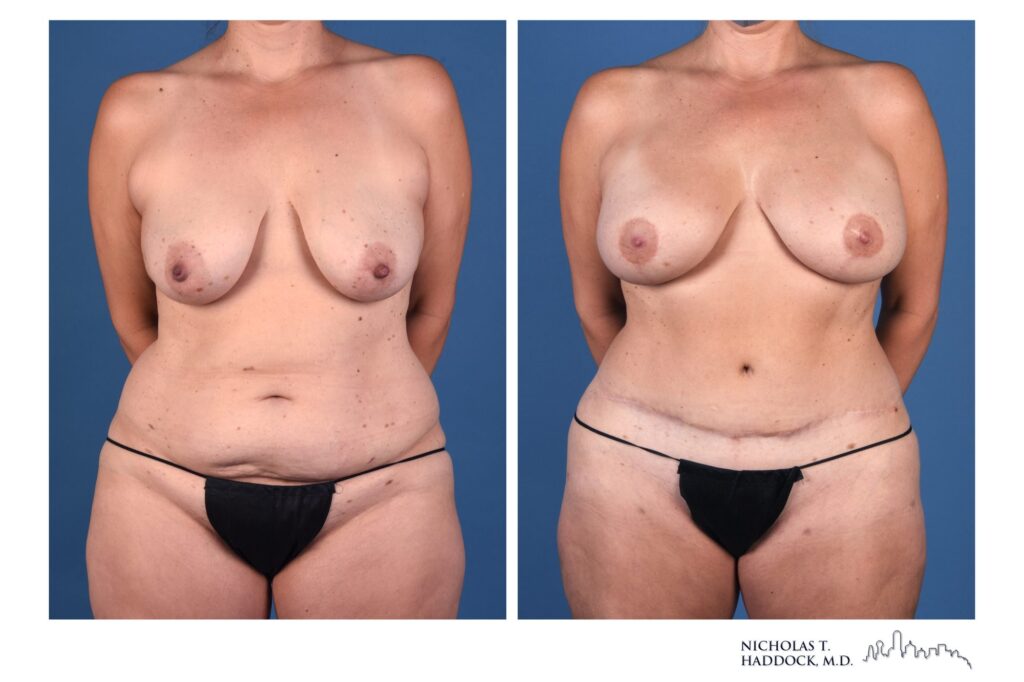
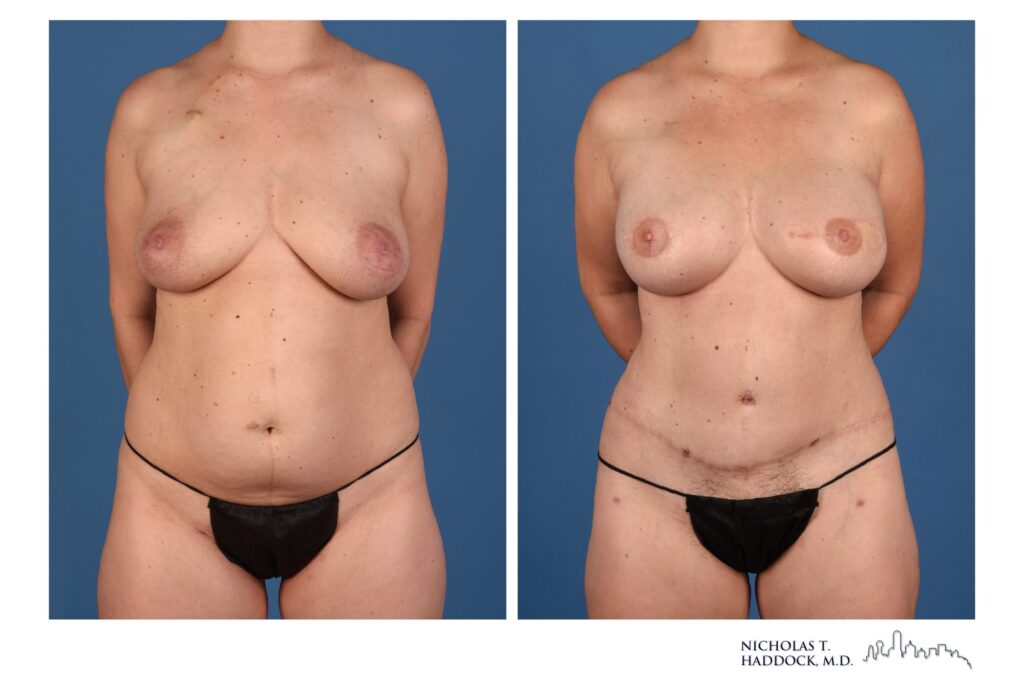
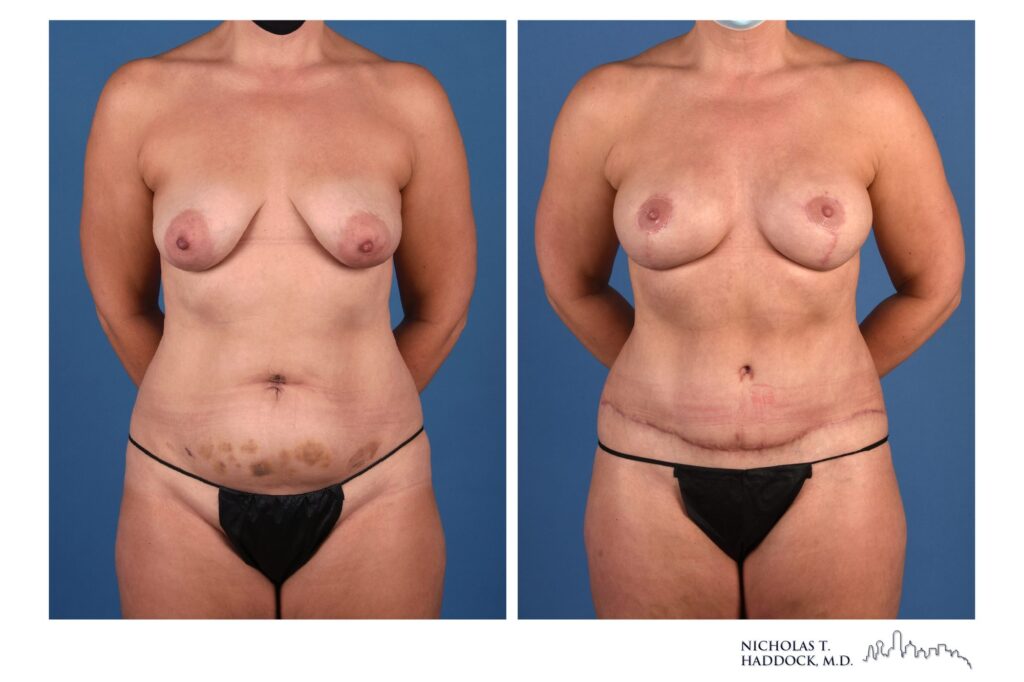
Individual results vary. Dr. Haddock posts a range of results to give patients a broad range of possible expectations. A large portion of the differences amongst results is a result of the patient anatomy and/or previous treatments. Photos are shared with each patient’s permission.
In microsurgery, experience is the variable that determines the result.
Choosing your surgeon
Dr. Haddock has performed approximately 2,500 DIEP flaps for breast reconstruction, with a flap success rate of greater than 99%. His approach is built around a few clear goals: superior aesthetic results, limited abdominal morbidity (fewer problems at the abdomen, where the tissue is taken, and the breast), and operative efficiency that leads to a quicker recovery. When you are choosing a surgeon for this operation, experience is key — and the focus of the operation can vary from surgeon to surgeon. Dr. Haddock does not view success as simply flap survival; his goal is to achieve the result each patient wants.
What recovery looks like
Dr. Haddock typically performs these operations at William P. Clements Jr. University Hospital in Dallas, using an Enhanced Recovery After Surgery (ERAS) protocol designed for a faster recovery and less postoperative discomfort.
- A one-night stay in the hospital
- Extra nursing care to monitor blood flow to the flap — on a regular hospital floor, not in an ICU
- About 6 weeks of restricted activity
- Some abdominal tightness — usually easing over the first 3–4 weeks
- Walking slightly flexed at the waist for the first 1–2 weeks
Printable instructions for your operation and your recovery:
- DIEP flap instructionsPDF
- Drain carePDF
- Medications to avoidPDF
- Protein supplementationPDF
- Scar managementPDF
DIEP flap, in more detail
Rectus diastasis (separated abdominal muscles)
Many women have a rectus diastasis — a separation of the two vertical abdominal muscles along the midline, most often after pregnancy or a significant change in weight. It can leave a bulge down the middle of the abdomen that exercise does not correct, because the problem is the gap between the muscles rather than the muscles themselves. The DIEP dissection already exposes the full width of the abdominal wall through the same low, bikini-line incision, so any separation can be assessed directly and closed during the same operation — no additional incision, and no second procedure. When a diastasis is present and repair is indicated, Dr. Haddock repairs it — every time. Because this is a perforator flap, the muscle itself is left intact: nothing is sacrificed from the abdominal wall to build the breast.
The belly button (umbilicus)
The umbilicus can be managed several ways during a DIEP flap. To limit complications, Dr. Haddock will sometimes remove the umbilicus (belly button) during the procedure — depending on a patient’s anatomy and health, this can reduce a 50–60% complication rate (mainly abdominal wound complications) to near zero. He has pioneered a technique for creating a new belly button (neo-umbilical reconstruction) that can be done at the time of nipple reconstruction or a later touch-up, often with a more natural aesthetic result than keeping the original belly button.
Double (stacked) DIEP flaps
When one breast needs more skin and volume — often in delayed reconstruction or after radiation — both sides of the abdomen can be used together for a single breast. Dr. Haddock and his partner have one of the largest published experiences with these procedures in the world.
Four-flap reconstruction
For patients in whom the abdomen or thighs alone won’t provide enough tissue, DIEP flaps from both sides of the abdomen and PAP flaps from both thighs can be performed at the same time. Using both donor sites avoids compromising the result and allows a more conservative surgery at each site. Dr. Haddock and his partner have one of the largest series of these procedures in the world.
Does insurance cover DIEP flap reconstruction?
Yes. If your mastectomy is covered by insurance, all forms of breast reconstruction should be covered as well. More on insurance coverage
What is a DIEP flap?
A DIEP (deep inferior epigastric perforator) flap is a natural-tissue (autologous) breast reconstruction that uses skin and fat from the lower abdomen. It takes only skin and fat; all of the muscle is preserved. The abdomen is closed much like a cosmetic tummy tuck (abdominoplasty), so most patients also get an improved lower-tummy contour.
Does a DIEP flap remove any abdominal muscle?
No. Dr. Haddock makes every effort to preserve the fascia (the strong lining of the abdominal wall), the nerves and the muscle fibers. In experienced hands, a DIEP flap can be done with minimal damage to the abdomen in most patients.
What do healed DIEP scars look like, and how do they change over time?
A healed DIEP scar fades with time and looks very similar to a cosmetic tummy-tuck scar. It can usually be placed in the underwear line, so it is not visible in a swimsuit or underwear. Walking slightly bent at the hips for the first 1–2 weeks protects the incision and improves the scar long term. Scar care can start about four weeks after surgery.
Are there problems that can show up years later?
The main later problem is weakness of the abdominal wall, usually described as a bulge in the lower abdomen. In experienced hands, this is very rare.
Can I have a DIEP flap after a C-section, liposuction, or other abdominal surgery?
Nearly always after a C-section. Generally after liposuction too, as long as the blood vessels are still usable and there is enough tissue for the reconstruction. Before a DIEP flap, Dr. Haddock routinely orders a CT scan with contrast of the abdominal wall. It confirms the blood vessels are present after any previous surgery, and whether you are a candidate.
How much time off work will I need, and when can I exercise again?
There are six weeks of restrictions: no exercise and no heavy lifting. You can often return to desk work within a few weeks, depending on how you feel and how motivated you are. Walking is encouraged right away. Light cardio can start after four weeks, and running, weights, golf and yoga after six. There is no driving for about 10–14 days, and not until you’re off prescription pain medicine and muscle relaxers. Your reflexes must also be fast enough to be safe, and everyone is different in how quickly they get there.
Will the reconstructed breast have feeling?
Feeling in the breast depends largely on the mastectomy. Some sensation can return over time, but you should be prepared for some numbness. Numbness of the lower abdomen is also common and usually fades with time.
In their words
“My experience was great with Dr. Haddock. His staff is so kind and his integrity and bedside manner is wonderful. Of course, the best part is the results.”
“You know you have a fantastic plastic surgeon when your breast oncologist does an exam, asks if you’re staying current on mammograms, then goes ‘oh wait… you had breast reconstruction.’ Your plastic surgeon is amazing! Well, I think so too.”
“I am a breast cancer survivor. When I look in the mirror I don’t see a daily reminder that I once had cancer — Dr. Haddock gave me results that make me feel so good about myself.”
“I had a DIEP flap and am very pleased with the results. Dr. Haddock discussed options that made me feel part of the process. I now refer others to him — not only for his surgical skill but for his caring nature.”
Hear from patients
Patients describing their DIEP flap reconstruction in their own words.
Potential complications
As with any procedure, there are risks associated with natural-tissue (autologous) breast reconstruction. The main adverse outcomes are total or partial flap failure. Total failure — the most feared complication — typically results from a clot in the vessels supplying the flap; with modern technique and in experienced hands, this risk is extremely low. Patients may also experience a hematoma (a collection of blood), a seroma (a collection of fluid), or wound-healing problems at either the donor or recipient site.
Videos, articles & resources
Medically reviewed by Dr. Nicholas Haddock, October 2026.
Considering DIEP flap reconstruction?
Tell us a little about yourself and Dr. Haddock’s office will reach out to help you schedule a consultation.
Request a Consultation