
Implant Breast Reconstruction
Rebuilding the breast with a breast prosthesis — most often as a staged process, beginning at the time of mastectomy.
Implant reconstruction, in brief
Implant reconstruction rebuilds the breast with a breast implant. This approach usually begins at the time of the mastectomy with a temporary tissue expander (a device that is gradually filled to stretch the skin), and is completed in two staged operations.
Dr. Haddock places the implant above the muscle — prepectoral — in nearly all patients. The one situation in which he might place it beneath the muscle is when a patient already has a submuscular pocket from a previous breast augmentation, and that is decided case by case.
When a tissue expander is used, Dr. Haddock is usually able to expand significantly at the time of the mastectomy itself. That gives the reconstruction shape and volume from the start, and it limits how many expansion visits are needed afterwards. Patients are often pleasantly surprised by the volume they have after the mastectomy.
Benefits and trade-offs
The principal benefit of using implants for breast reconstruction is that it is a relatively straightforward method that can limit the surgical site to the breast — there is no second site on the body from which tissue has to be taken.
Aesthetically, implants can provide a rounder-shaped breast. This is especially true at the upper breast.
Implant reconstruction does, however, have functional downsides, and they are worth understanding before you choose it. The implant can sometimes be felt, and its imperfections can sometimes be seen, through the skin of the breast. How much so depends largely on the thickness of the mastectomy flaps — the skin and tissue left behind after the breast is removed — which is not something either you or your surgeon fully controls. And an implant reconstruction is always less natural in shape and consistency than a natural breast.
Implants are also not lifelong devices. You will likely need one or more procedures to replace the implant over your lifetime.
Most patients who undergo implant reconstruction also have an awareness of having implants. Simple things like bumping into a wall, or giving someone a hug, will allow you to feel the implants. And an implant cannot warm itself — if it is cold outside, it can feel cold.
Dr. Haddock is best known for microsurgical breast reconstruction — but he performs more breast reconstruction with implants than with flaps.
One operation, or two?
Most implant reconstructions are done in two stages. A tissue expander is placed at the time of the mastectomy and gradually filled over a series of clinic visits; at a second, smaller operation the expander is exchanged for the more permanent implant.
When Dr. Haddock considers direct-to-implant
Direct-to-implant — placing the more permanent implant at the time of the mastectomy, in a single operation — is something Dr. Haddock considers in specific patients. He will do it in any situation where a single surgery is preferred for medical reasons. He will also consider it in very thin patients who are not candidates for fat grafting at a later operation. In either case you also have to be comfortable with your current size.
Why two stages is usually the better result
At the time of a mastectomy the implant cannot be placed overly tight. Doing so puts pressure on the mastectomy flap — the skin and tissue left behind after the breast is removed — which can restrict its blood supply (ischemia). Some of that skin may then not survive. A single-stage reconstruction can look very good in the early postoperative period, but over the longer term the tissues soften and the imperfections of the device, such as rippling, can become more visible.
A two-stage approach lets Dr. Haddock place a slightly larger and tighter implant at the second stage, once the mastectomy skin has healed. It also allows fat grafting at that second operation, which improves the soft-tissue coverage over the upper part of the implant.
Before & After
Front views from seven of Dr. Haddock’s implant reconstructions — before on the left, after on the right.
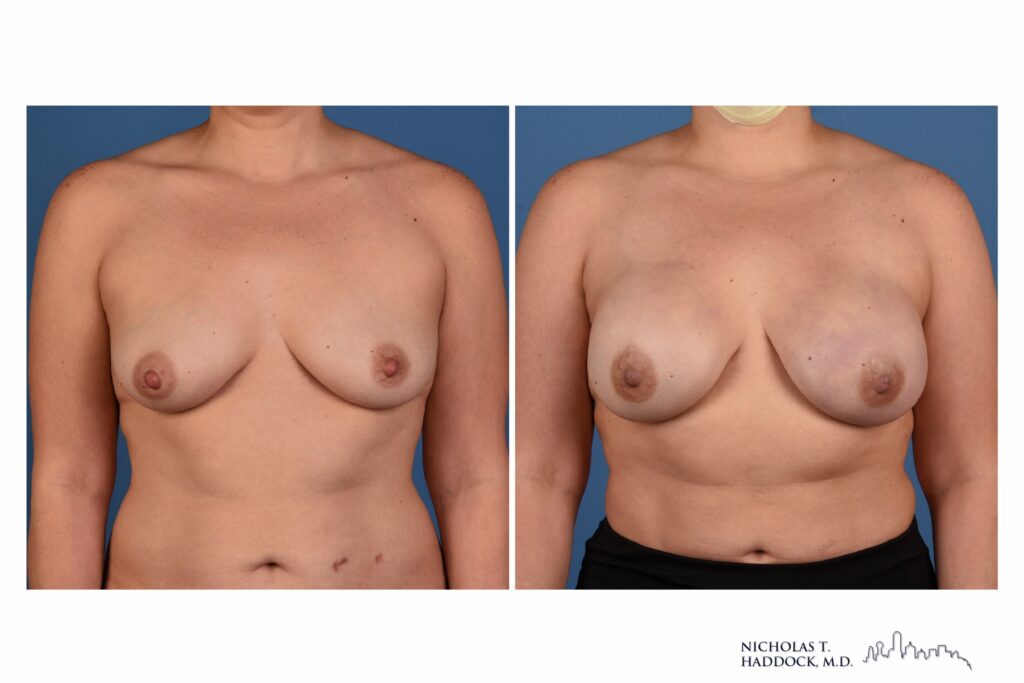
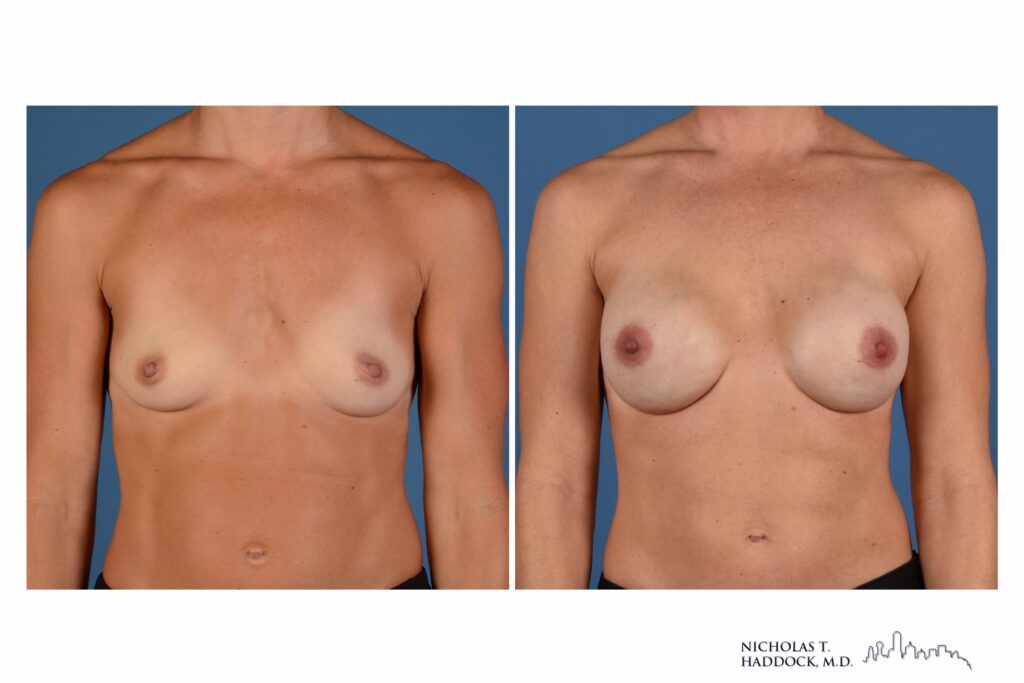
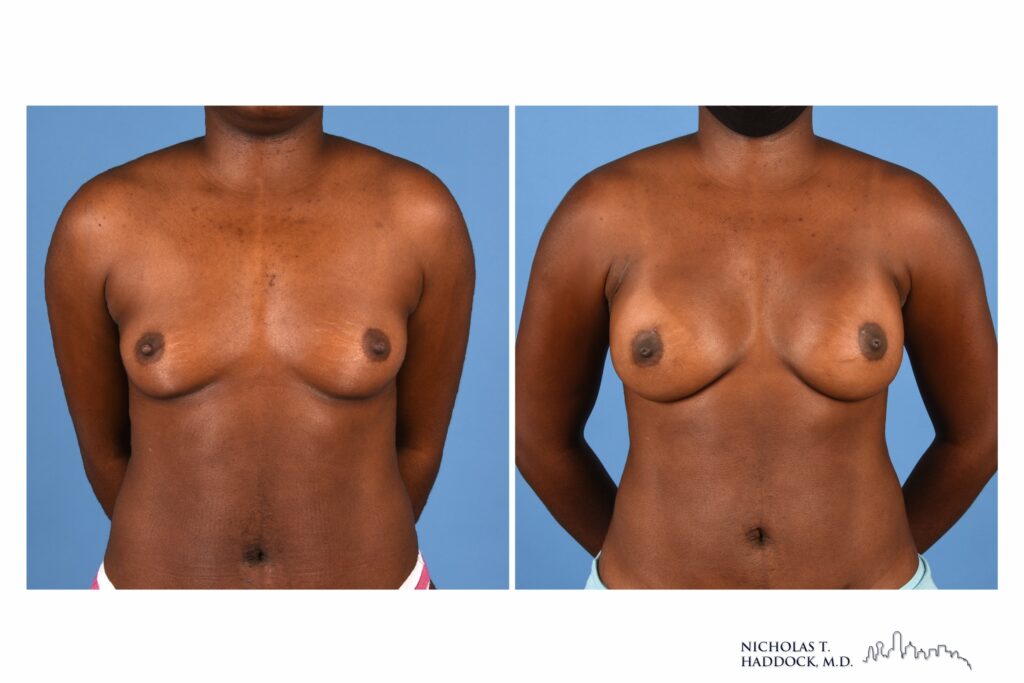
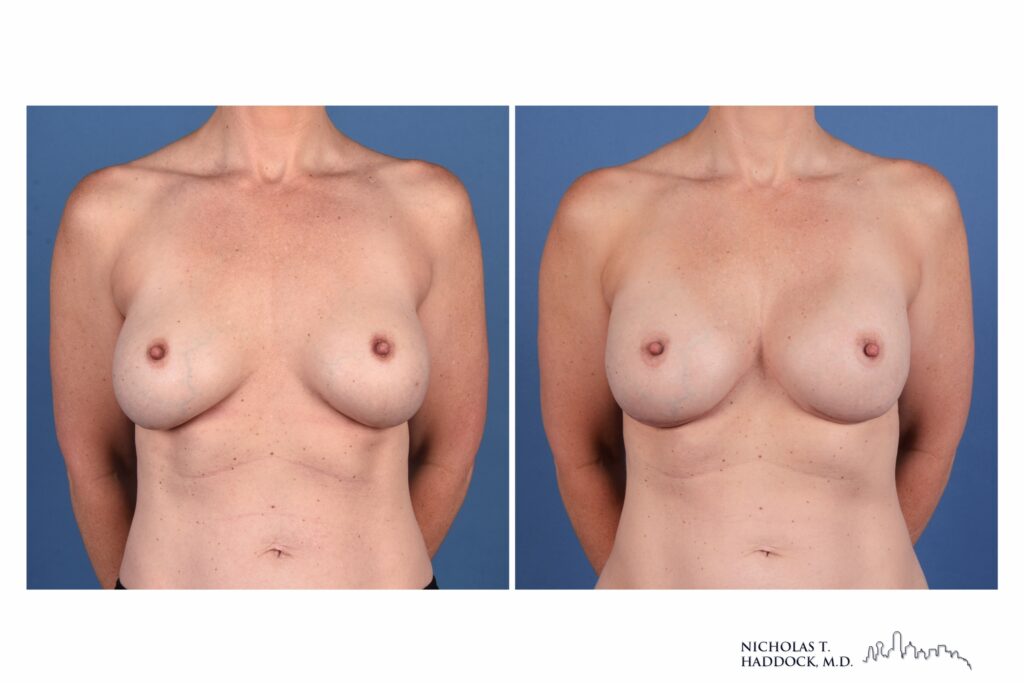
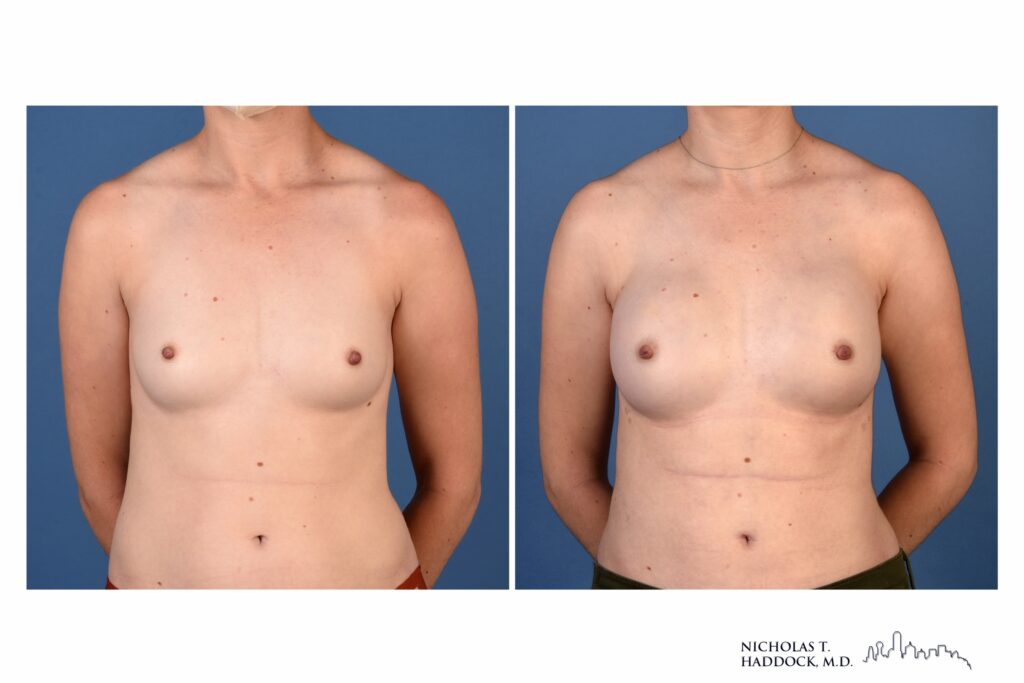
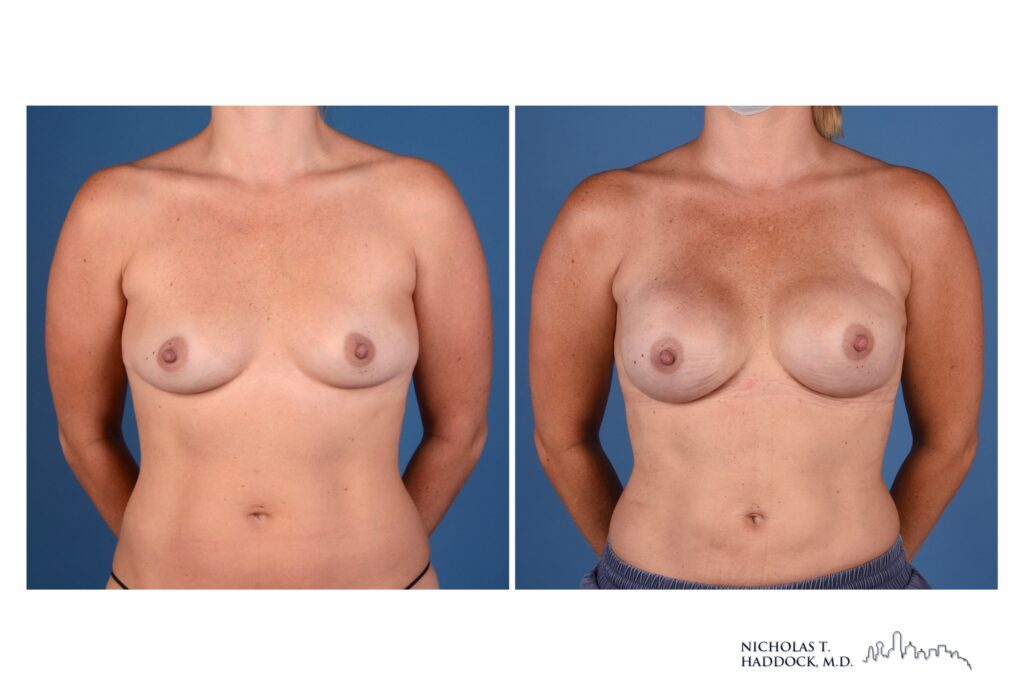
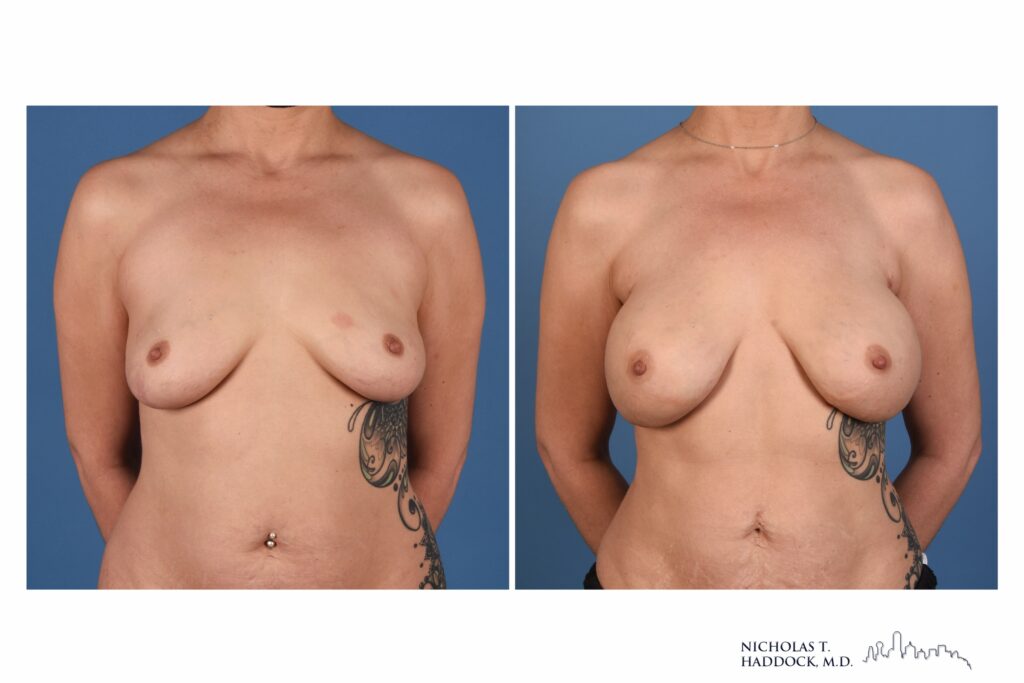
Individual results vary. Dr. Haddock posts a range of results to give patients a broad range of possible expectations. A large portion of the differences amongst results is a result of the patient anatomy and/or previous treatments. Photos are shared with each patient’s permission.
Implant revision surgery
If you already have implants and would like the result changed or improved, see Revision & Secondary Procedures.
Fat grafting
Dr. Haddock routinely offers fat grafting to his implant reconstruction patients. Fat is removed by liposuction from an area of unwanted fat, processed to remove extra tissue and fluid, and then injected around the implant.
The purpose is twofold: a better aesthetic result, and a more natural feel — the grafted fat adds a layer of your own soft tissue over the implant, and the thickness of that tissue is what determines how palpable an implant is. Dr. Haddock typically offers it at the time of implant exchange and at the time of nipple reconstruction.
What recovery looks like
Implant reconstruction is usually two operations, and they recover differently. The first — placing the expander at the time of the mastectomy — is the larger of the two. The second, exchanging the expander for the implant, is outpatient and is generally tolerated very well, usually with minimal pain, though that depends on the details of the procedure.
Stage one — the expander, at the time of your mastectomy
- Many patients go home the same day. Some stay one night in the hospital after a mastectomy.
- Two small drains are placed in each breast, and typically come out by about two or three weeks.
- Nothing over ten pounds for four weeks. Gentle arm range-of-motion exercises start the day after surgery.
- Light cardiovascular exercise can begin after four weeks. You can return to all activities without restriction after six weeks.
- Tightness across the chest is normal. Numbness of the breast skin is also expected after a mastectomy, because most of the nerves to that skin are cut as part of the mastectomy itself.
Between the stages — expansion
Dr. Haddock partially fills the expander in the operating room, which is why the reconstruction has shape from the start. Expansion resumes in clinic about two to three weeks later, once the incisions have healed and your pain is manageable. The expander’s fill port is found with a magnet, and the expander is filled through a small needle. Most patients do not feel the needle, but may feel additional tightness the night of the expansion. The schedule is tailored to you and is usually weekly or every other week. If you are told you will need radiation, expansion is sped up so that it is finished before your radiation planning session (simulation) for treatment.
Stage two — exchanging the expander for the implant
- Outpatient surgery. The implant portion is tolerated very well, usually with minimal pain.
- Most patients do not need drains at the exchange. When drains are used, they typically do not stay in as long as the drains from the expander operation.
- Nothing over ten pounds for four weeks.
- Light cardiovascular exercise can begin after four weeks. You can return to all activities without restriction after six weeks.
- The implants settle over time; the shape in the first weeks is not the final shape. If you have had radiation, expect that asymmetry will be more pronounced and will take longer to settle — and it may be permanent.
Recovery after a revision
From a recovery standpoint, an implant revision is often very similar to the expander-to-implant exchange described above. That is less true when the revision involves significant work on the capsule (the scar tissue around the implant), a change of pocket, or the addition of acellular dermal matrix (ADM) — in those situations Dr. Haddock typically places drains.
Printable instructions for your operation and your recovery:
- Tissue expander placementPDF
- Tissue expander exchange to implantPDF
- Implant exchangePDF
- Liposuction and fat graftingPDF
Implant reconstruction, in more detail
Saline or silicone?
Dr. Haddock prefers silicone, because it is more natural. Both types have a silicone shell; a silicone implant is filled with a silicone gel, and a saline implant is filled with salt water. Silicone implants tend to be smoother and to feel more natural. Saline implants tend to feel more like a water balloon, and often look less natural. He does not recommend saline implants — but if a patient is adamant about it, he will use them.
What is an “internal bra”?
Dr. Haddock uses a range of support materials alongside implant reconstruction — what some people call an internal bra. Some are placed at the time of tissue expander placement; others are added later. Some are used to cover the implant, so that its edges and any rippling are less visible. Others are used to support the implant against gravity, so the reconstruction is less likely to descend over time. Which material is used, and when, is tailored to the individual and to what that particular situation needs.
Do you use shaped implants?
No. Dr. Haddock no longer uses shaped implants. All shaped implants are textured, and because of the risk associated with textured implants, he does not use them.
How long does each stage take?
Placing tissue expanders takes about 1 hour for both sides, less for one side. Exchanging the expanders for implants usually takes 1 to 1.5 hours.
What to know about the implant itself
Breast implants are regulated medical devices, and the manufacturer publishes a patient checklist that you will be asked to review before surgery. The points below are drawn from that document. They are the manufacturer’s statements about its own devices — not results from Dr. Haddock’s practice.
- Breast implants are not lifetime devices. The longer they are in place, the more likely it becomes that they will need to be removed or replaced.
- BIA-ALCL — breast implant-associated anaplastic large cell lymphoma — is an uncommon cancer of the immune system that has been linked to breast implants. The great majority of reported cases have occurred in patients with textured implants; reports in patients who have only ever had smooth implants are rare. Dr. Haddock uses smooth implants. BIA-ALCL typically develops years after surgery, and usually shows up as swelling, a fluid collection, a lump or pain in the breast. When it is found, it is most often treated successfully by removing the implant and the surrounding capsule.
- Some patients with breast implants report a group of systemic symptoms — most often joint pain, muscle aches, fatigue, and difficulty concentrating. This is commonly called breast implant illness, and it appears in the manufacturer’s checklist for that reason. Large population studies have not shown that implants cause these symptoms, and there is no diagnostic test for it. Some patients who have their implants removed report that they feel better. If this concerns you, bring it up at your consultation.
- Silicone implants call for imaging follow-up even if you feel fine: a first ultrasound or MRI at five to six years after the initial implant surgery, then every two to three years after that, and an MRI sooner if you have symptoms or the ultrasound is uncertain.
What the manufacturer reports at ten years
The figures below are not Dr. Haddock’s results, and they are not results from this practice. They are one implant manufacturer’s own data, reported at ten years of follow-up, and they combine cosmetic augmentation and reconstruction patients. Each one is the largest complication rate the manufacturer reported in that study — not an average, and not what most patients experience. They are here because you will see them on the checklist you are asked to sign.
- Reoperation — up to 71.5%. Any further operation, for any reason, over ten years.
- Rupture or leaking — up to 35.4%.
- Capsular contracture, Baker grade III or IV — up to 28.7%. Painful or tightening scar tissue around the implant.
- Implant malposition — up to 13.3%. The implant shifting out of position.
- Wrinkling or rippling — up to 10.2%.
- Implant palpability or visibility — up to 6.7%. Being able to feel or see the edges of the device.
The latissimus flap
Where the latissimus flap fits
The latissimus dorsi flap moves skin and muscle from the back around to the chest on its own blood supply, without microsurgery. In Dr. Haddock’s practice it is a rarely used add-on or rescue (salvage) procedure rather than a routine one — he uses it for complex wounds, in the setting of radiation, and to salvage an implant reconstruction. It does not usually carry enough bulk on its own to rebuild a moderate-sized breast, so an expander or an implant is generally still required alongside it.
Hear from patients
Patients describing their implant reconstruction in their own words.
Videos, articles & resources
Medically reviewed by Dr. Nicholas Haddock, October 2026.
Considering implant reconstruction?
Tell us a little about yourself and Dr. Haddock’s office will reach out to help you schedule a consultation.
Request a Consultation