
Dallas Breast Reconstruction
Dr. Nicholas Haddock performs every type of breast reconstruction — implant-based, natural-tissue flaps, and combinations of the two — so the plan can be built around you rather than around one technique.
Breast reconstruction is an integral part of the treatment of breast cancer. It can happen at the time of mastectomy or at a later date as a separate operation.
The timing depends on a variety of factors. These may include your own wishes, desires and goals, the type and size of the tumor, and the possible need for post-operative radiation therapy or chemotherapy. You make these decisions in consultation with your breast surgeon, your oncologist and your plastic surgeon. At our Dallas breast reconstruction center we will guide you through this process.
The overall goals of breast reconstruction are to create a breast shape, to achieve a normal and even (symmetric) silhouette, to limit complications and the physical toll on you, and to avoid the need for an external prosthesis. In more recent years those goals have progressed to achieving improved aesthetic results regardless of the route taken. Breast reconstruction can be divided into three broad categories: implants with or without tissue expansion, autologous (your own) tissue, and a combination of implants and autologous tissue. Whichever type of reconstruction is chosen, it typically requires more than one procedure to complete.
It is very important to make sure all available options for breast reconstruction are presented and discussed. Dr. Haddock performs all types of breast reconstruction and can guide you to an individualized and informed decision.
The timing of breast reconstruction
Breast reconstruction can occur either at the time of mastectomy or at some point after the mastectomy is completed. These two time frames are referred to as immediate and delayed reconstruction.
Most surgeons agree that the aesthetic result and the technical ease are improved in an immediate breast reconstruction compared with a delayed one. At centers that perform immediate breast reconstructions, the breast cancer surgeons typically use nipple-sparing or skin-sparing mastectomies, which preserve the breast skin (and, in a nipple-sparing mastectomy, the nipple). These methods allow for local control of the breast cancer while preserving the breast boundaries. When breast reconstruction is performed in the immediate setting there is no scar tightening to overcome, and the preserved breast skin helps maintain the natural borders of the breast. By preserving that natural skin brassiere, the reconstruction is more straightforward and leads to a result that is potentially more symmetric with the other breast when only one breast is being reconstructed.
In delayed reconstruction the natural borders no longer exist. The plastic surgeon must recreate the mastectomy defect and redefine the borders. The quality of the chest skin has to be critically evaluated: if you have had radiation to the chest wall, the resulting scarring and skin tightening may limit how far the breast projects forward and how naturally it hangs (ptosis of the breast). That may make the skin difficult to expand, or may require recruiting skin for the breast from another part of the body.
In many situations Dr. Haddock uses what is termed a delayed-immediate approach. This involves placing a tissue expander (a temporary implant that holds and stretches the space) at the time of the mastectomy, which can then be converted to your own tissue (DIEP flap, PAP flap, or LAP flap) in a delayed fashion. It keeps the focus at the time of the mastectomy on your cancer care: because the definitive reconstruction happens as a separate step, neither the cancer treatment nor the reconstruction has to be compromised to accommodate the other. If you have not yet decided on the route for definitive reconstruction, this approach also allows more time to make that decision, and more control over the breast shape and the long-term cosmetic result. Dr. Haddock will discuss the options at length so that you are completely comfortable with your choice.
Overall, breast reconstruction — with implants or with autologous tissue — improves quality of life by restoring your sense of self and body image. It does not hinder the treatment of the cancer, and it does not impact recurrence rates. Breast reconstruction has been shown to aid in the total recovery of the breast cancer patient through both physical and mental rehabilitation.
Dallas breast reconstruction options
In modern breast reconstruction there are a number of options. That is a real advantage over previous years, but it can also be overwhelming to choose between them. The simplest way to think about it is in terms of three choices: you can choose to undergo breast reconstruction with an implant, with your own tissue, or with a combination of an implant and your own tissue. The most common methods in Dr. Haddock’s practice are implants, DIEP flaps, LAP flaps, and PAP flaps. He also offers lateral thigh perforator (LTP) flaps and superior gluteal artery perforator (SGAP) flaps when they are the better fit for a particular patient.
Implant Reconstruction
A breast implant, most often placed above the muscle, either directly at mastectomy or after a period of tissue expansion. Implant breast reconstruction →
DIEP Flap
Skin and fat from the lower abdomen, moved with its own blood supply and no abdominal muscle sacrificed. DIEP flap breast reconstruction →
PAP Flap
Tissue from the upper inner and back of the thigh — the usual choice when the abdomen is not available or not preferred. PAP flap breast reconstruction →
LAP Flap
Tissue from the lower back and flank, used when neither the abdomen nor the thigh will provide what is needed. LAP flap breast reconstruction →
Where the tissue comes from
When reconstruction uses your own tissue, the incision is placed at the donor site rather than only on the breast. The DIEP flap takes skin and fat from the lower abdomen, along a line similar to a tummy-tuck scar. The illustrations below show each donor site Dr. Haddock uses, and where each incision sits.
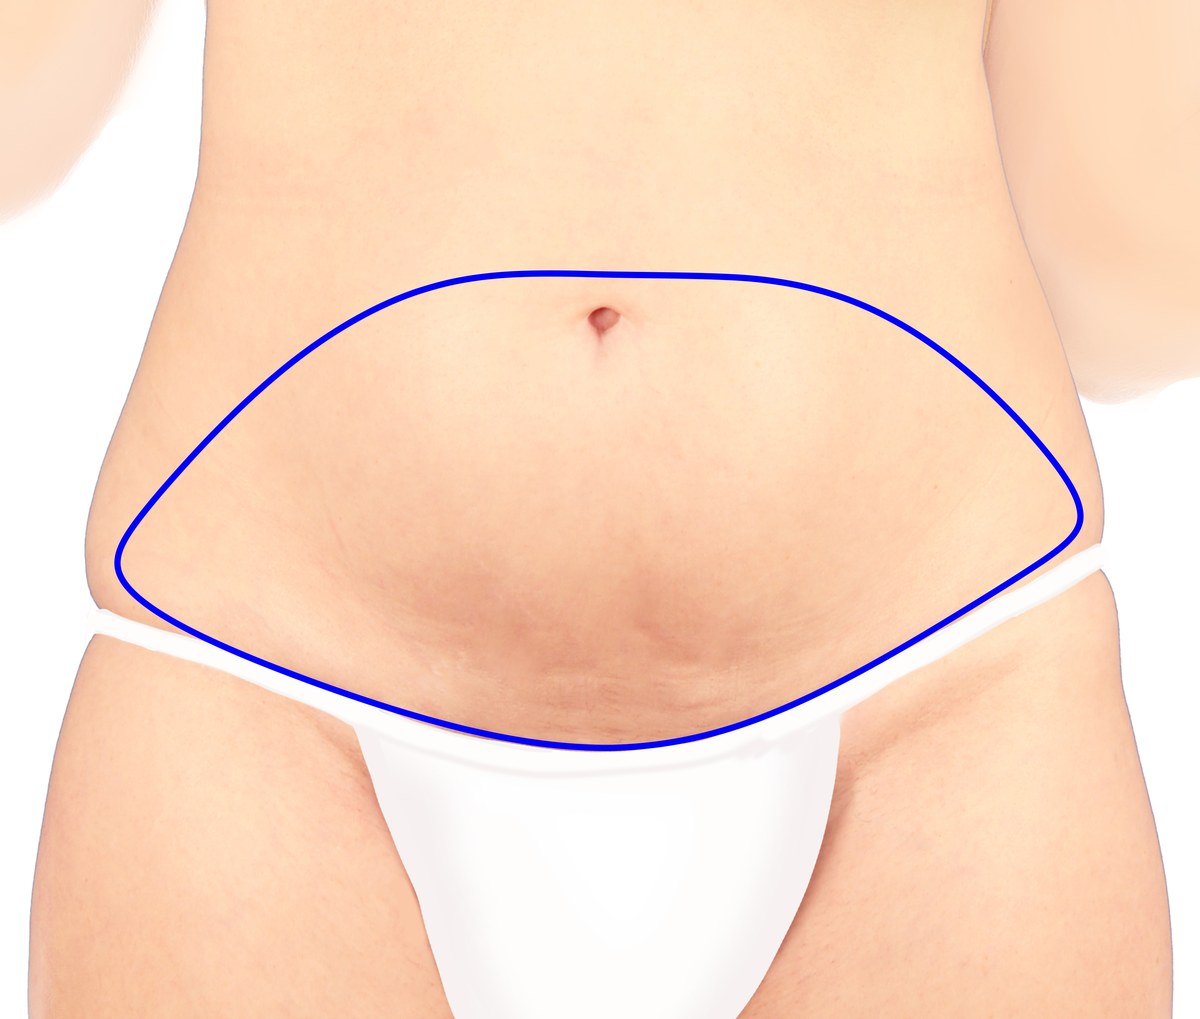
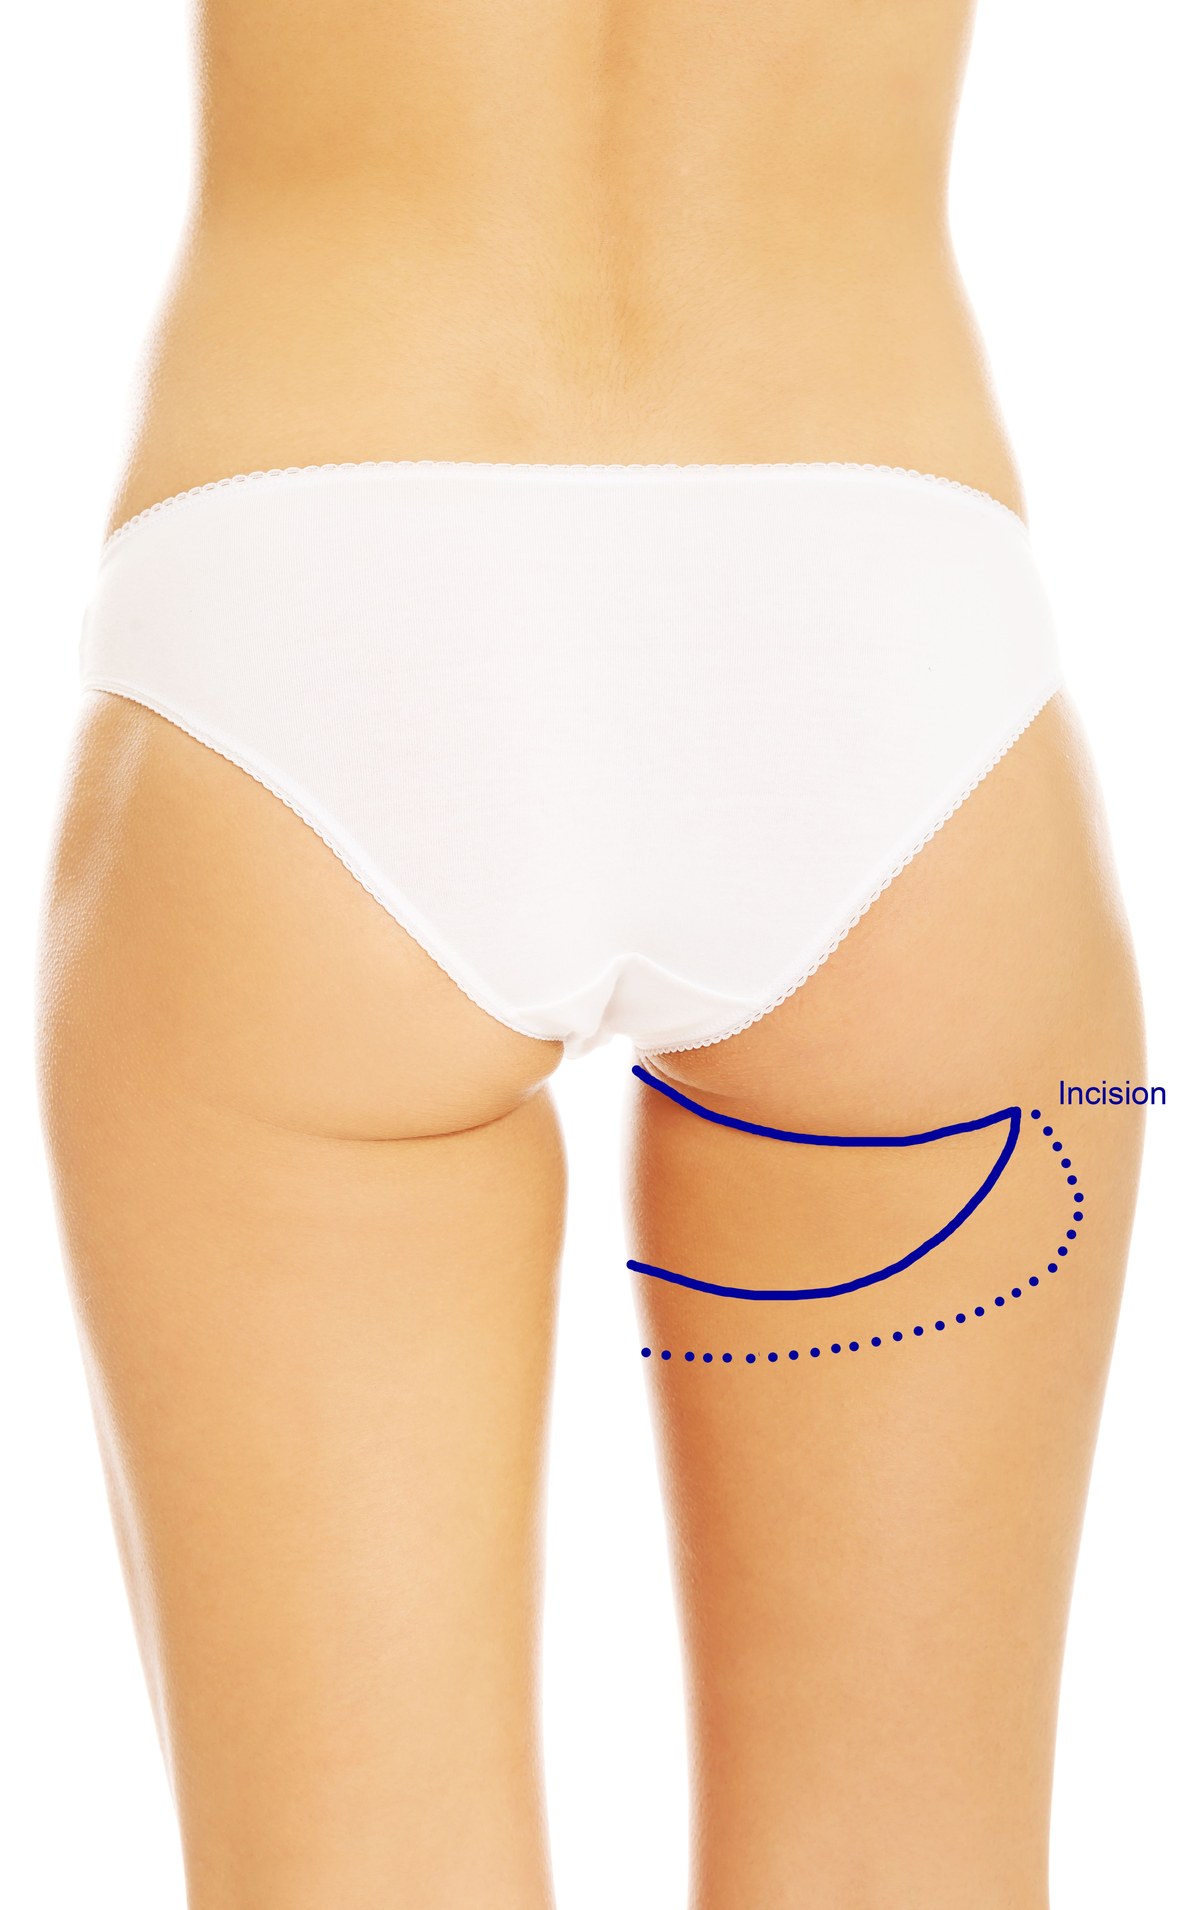
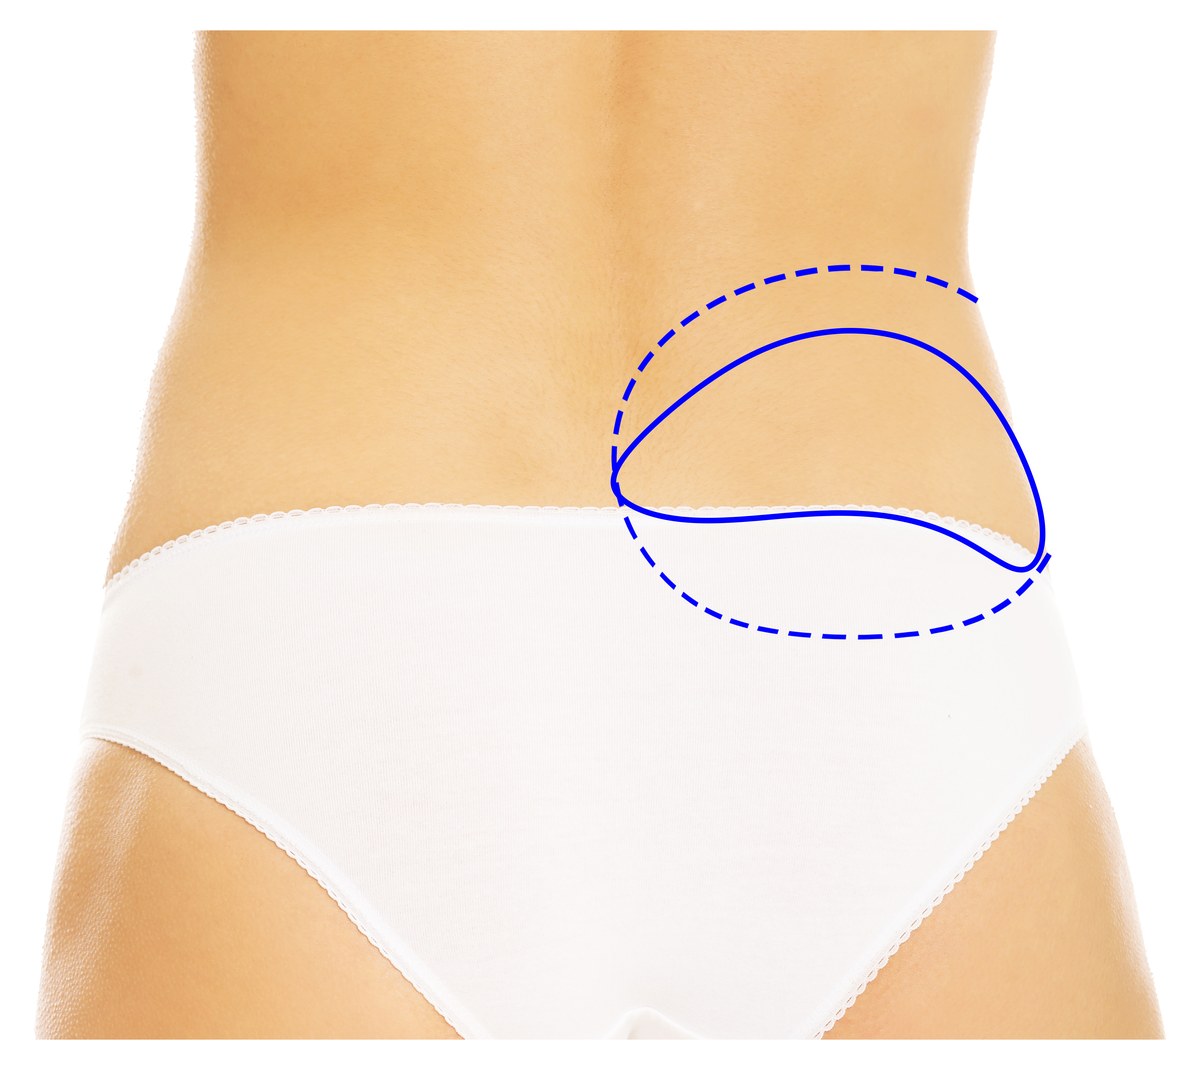
Breast reconstruction and breast cosmetic surgery are the focus of Dr. Haddock’s practice.
Choosing a surgeon for breast reconstruction
Whichever route you choose for breast reconstruction, it is important to ask questions and to be fully comfortable with your surgeon. You should also make sure your surgeon is experienced in breast reconstruction and is passionate about this work. Dr. Haddock has performed thousands of breast reconstruction procedures and has presented at multiple regional, national and international meetings on breast reconstruction. Experience on that scale does not make any of it routine: he still approaches every patient as an individual, and the focus stays on what you specifically need rather than on the operation he performs most often.
In our Dallas breast reconstruction center we offer state-of-the-art treatment with the most advanced methods of reconstruction available. Most surgeries are performed at William P. Clements Jr. University Hospital, where we have specialized teams and hospital units that focus on our breast reconstruction patients.
We have a coordinated approach designed to provide the best experience possible. That includes an enhanced recovery after surgery (ERAS) protocol for both tissue-expander surgery and all flap-based surgery. These pathways have significantly decreased the pain medication our patients require and shortened their length of stay.
We also care for a number of patients who travel from elsewhere in Texas, and from out of state, for Dallas breast reconstruction. We are happy to help you plan that visit — from the first consultation through the post-operative visits.
Nipple-areolar complex reconstruction
Reconstruction of the nipple-areolar complex (the nipple and the darker circle of skin around it, the areola) is an important component of a complete breast reconstruction, since the nipple is the central focus when viewing the breast. For many patients it is the step that makes the result feel finished. Most methods of mastectomy remove the nipple-areolar complex along with the breast tissue, because the nipple contains extensions of the milk ducts that are themselves at risk for disease. The initial post-operative reconstruction is therefore left without a nipple.
For the best result Dr. Haddock recommends either a nipple reconstruction together with an areolar 3D tattoo, or at a minimum a 3D tattoo for the entire nipple-areolar complex. This is typically performed about three months after the size and shape of the breast are as desired. If you are concerned about how much the reconstructed nipple will project, that can be tailored — within the limits of your own tissue. How much projection can be built depends on the thickness of the tissue at the site: making the nipple smaller is generally straightforward, while making it larger is not always possible. Where tissue thickness limits what surgery can achieve, a 3D tattoo can enhance the appearance of projection — without the nipple projecting through clothing.
Although most forms of mastectomy remove the nipple-areolar complex, a nipple-sparing mastectomy removes the breast tissue but spares the nipple and areola. A discussion with your surgical oncologist will determine whether you are a candidate for that procedure. If you are not, nipple-areolar complex reconstruction is often an important part of how satisfied patients are with the cosmetic result of the breast reconstruction overall.
Patient comments about breast reconstruction with Dr. Haddock
“You know you have a fantastic plastic surgeon when your breast oncologist conducts exam and ask if you are staying current on mammograms and then goes “oh wait… You had breast reconstruction. Your plastic surgeon is amazing!” Well, I think so too. Thanks Dr. Haddock!”
“I can truly say that my experience has been wonderful. Dr. Haddock is a great plastic surgeon who takes pride in his work and makes you feel you are in good hands. He is always there to answer any question or concern. I truly recommend him for any type of plastic surgery because he loves what he does and he is good at it.”
“I am a breast cancer survivor!! And I can truly say that when I look in the mirror I don’t see a daily reminder that I once had cancer that took away the old models of my breast because Dr. Haddock gave me new models that make me feel so good about myself!!”
“I had a DIEP flap and am very pleased with the results. Dr. Haddock was very kind and wanted to make sure I was happy with the results. He discussed options with me that made me feel like I was part of the process. I now refer others to him. I highly recommend him, not only for his surgical skills but also for his caring nature.”
“My experience was great with Dr. Haddock. His staff is so kind and his integrity and bedside manner is wonderful. Of course, the best part is the results.”
“The amazing, caring, genius, artist, surgeon….the only….Dr. Haddock. I am blown away by the standard of care I received by this incredible doctor and his staff.”
“Now I have a better body then I did going into cancer treatment.”
“Dr. Haddock said you’ve got some room on the back of your legs that I could take off, and I was like, ‘OK, that’s kind of a no brainer. This was almost like a mommy makeover.”
“Thanks to you Dr Haddock and your staff who I love so much! Thank you for participating in this journey with me and for taking such good care of me and for sharing my story! From day one, I knew you were my “person”. Not many doctors make you feel like you’re their only patient-and that’s how I felt with you. You took the time to listen to me, to answer my questions, and you guided me but allowed me to make my own decisions. I’m so pleased with my “new normal” and I can’t thank you enough for putting me back together so beautifully!”
Videos, articles & resources
Medically reviewed by Dr. Nicholas Haddock, October 2026.
Considering breast reconstruction in Dallas?
Tell us a little about yourself and Dr. Haddock’s office will reach out to help you schedule a consultation.
Request a Consultation