
LAP Flap Breast Reconstruction
Natural-tissue breast reconstruction using your own skin and fat from the lower back — a newer operation, performed by only a few teams in the world.
The Lumbar Artery Perforator flap (LAP flap) rebuilds the breast using skin and fat borrowed from the lower back. The tissue is lifted with its own small blood vessels, moved to the chest, and reattached under a microscope to vessels at the mastectomy site.
The blood vessels supplying this tissue travel close to the spine. To avoid dissecting near important nerves, those vessels are deliberately kept short. That means a short additional length of blood vessel is needed. That length most often comes from the lower abdomen, through a small separate incision similar to a C-section. Other sources are available when needed.
Like the other flap operations, a LAP flap can improve the contour of the area the tissue is taken from — in this case the flanks and lower back. In some patients there is also the illusion of a buttock lift.
Why natural-tissue reconstruction
- It is permanent. The reconstruction is built from your own living tissue, so once it has healed it is simply part of you — there is nothing to exchange or replace later.
- It looks and feels natural. The reconstructed breast has the softness and movement of the tissue it is made from, and it typically blends into the chest rather than sitting on it.
- It is living tissue with its own blood supply. That means it stays at body temperature — it does not turn cold when the weather does, the way an implant can.
- It changes with you. Gain weight and the reconstruction gains with you; lose weight and it does the same. It follows your body over time instead of staying fixed.
- It stays fat — it never becomes breast tissue. The tissue that is moved is skin and fat, and it remains skin and fat, so it does not change your risk of breast cancer.
These advantages are shared by every natural-tissue reconstruction Dr. Haddock performs — DIEP, PAP, and LAP alike. Which donor site is right for you is a separate question, decided together after examination and imaging.
Why the lower back
- The donor site gives a contour improvement to the flanks and lower back, and in some patients the illusion of a buttock lift.
- The incision sits across the lower back, where it is covered by almost anything you wear.
- It opens a donor site that is independent of the abdomen and the thighs, so previous surgery or previous reconstruction at those sites does not rule it out.
- When both breasts are being reconstructed, Dr. Haddock often does both sides in a single operation rather than staging them weeks apart — a decision made case by case, based on your anatomy and medical history.
- Like all perforator flaps, it takes only skin and fat — the muscle is left in place and its function preserved.
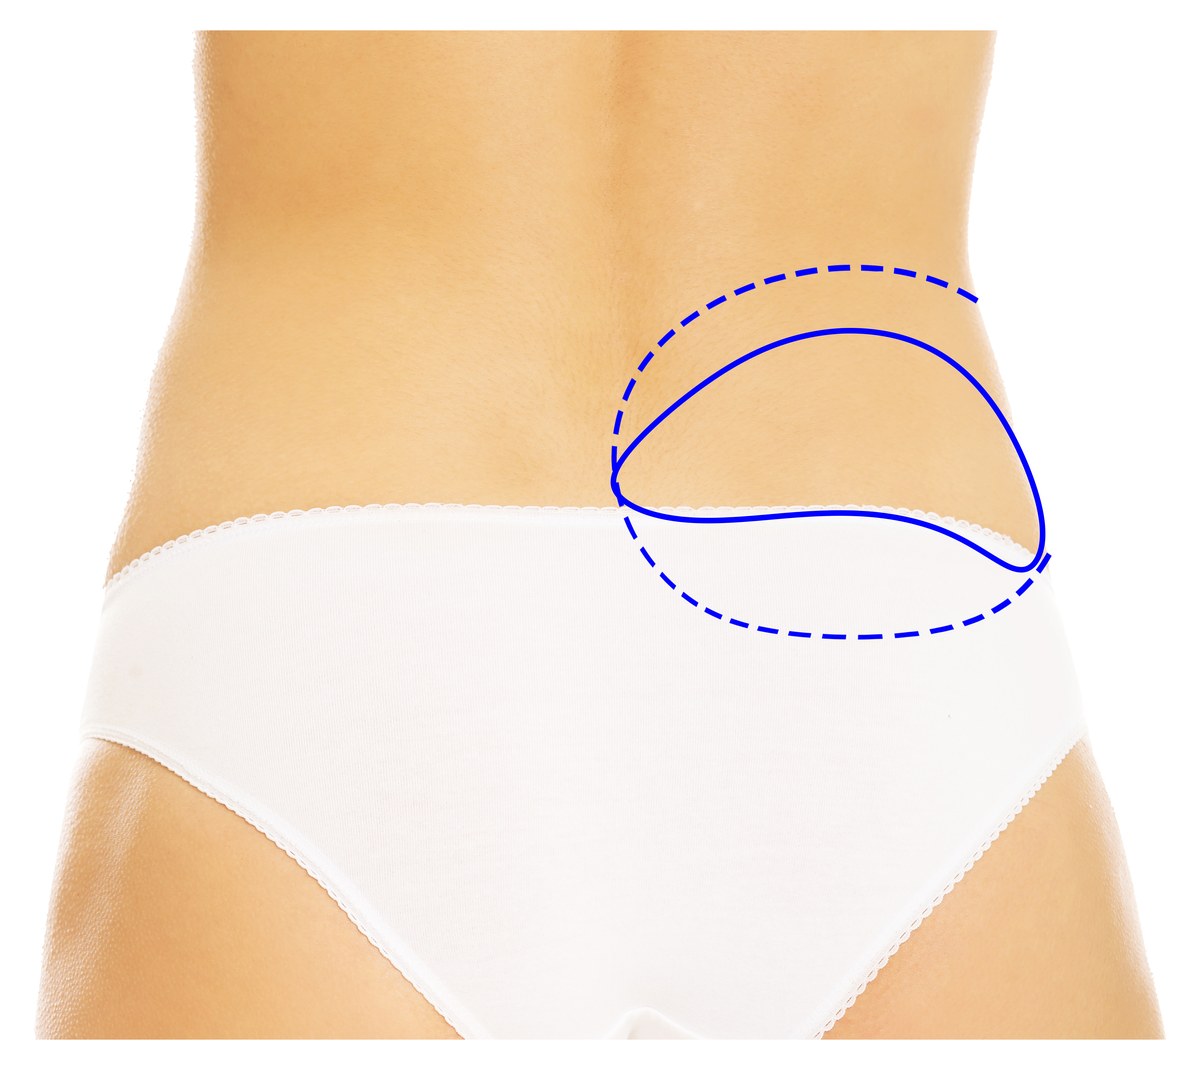
The tissue is taken from the lower back and flank, and the incision runs across the lower back. It sits low enough that ordinary underwear or a waistband covers it.
The diagram shows the back only. A LAP flap also needs a small separate incision to obtain the extra length of blood vessel described above — most often on the lower abdomen.
Before & After
Three of Dr. Haddock’s LAP flap reconstructions — before on the left, after on the right.
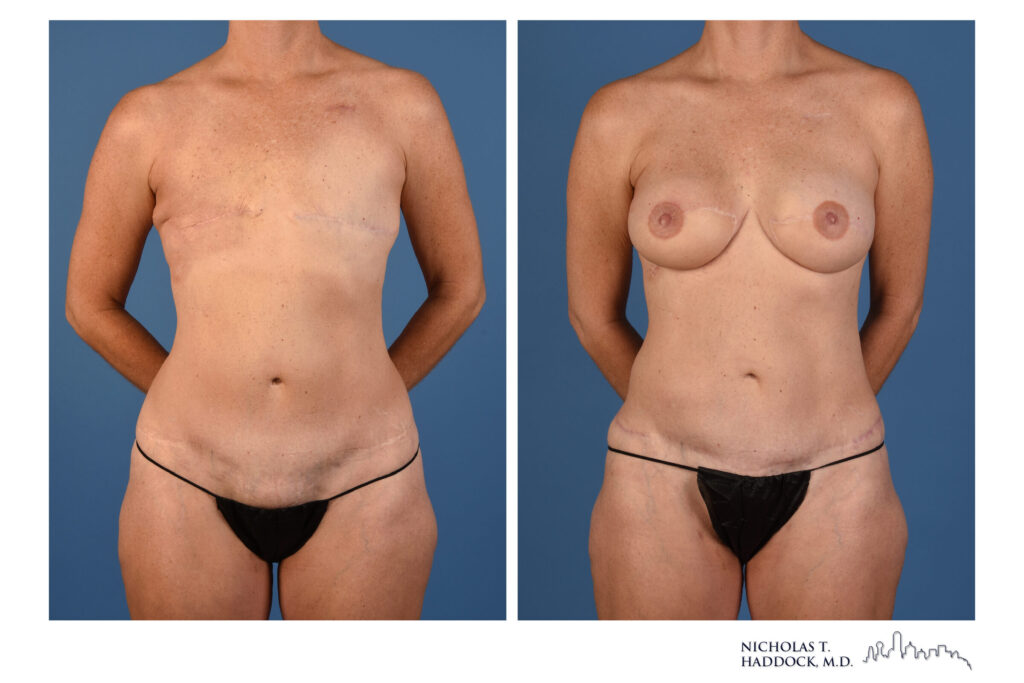
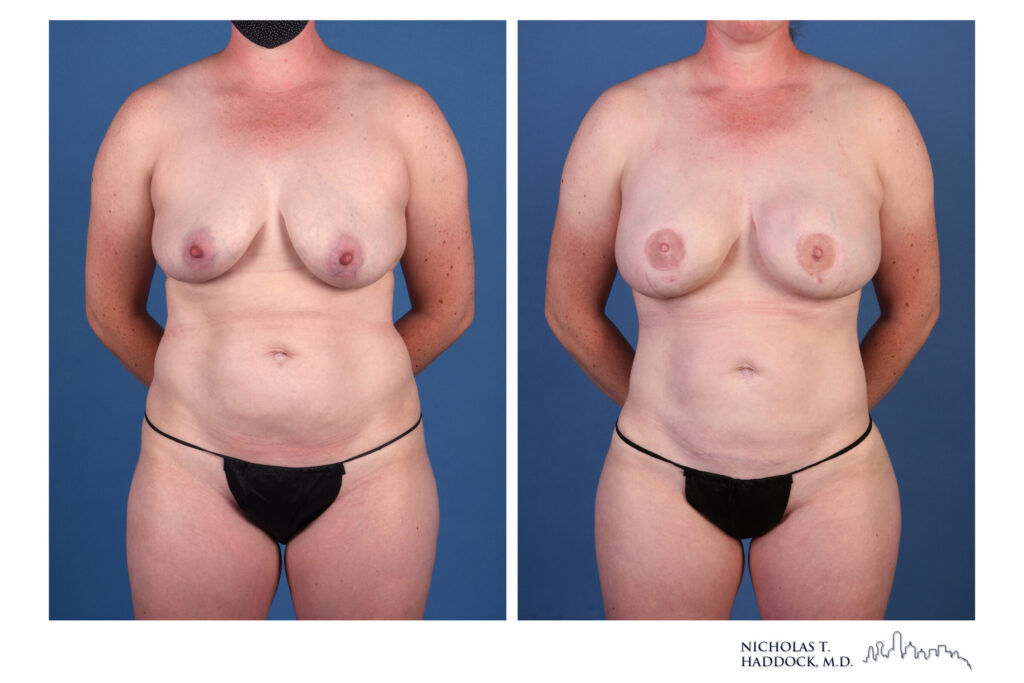
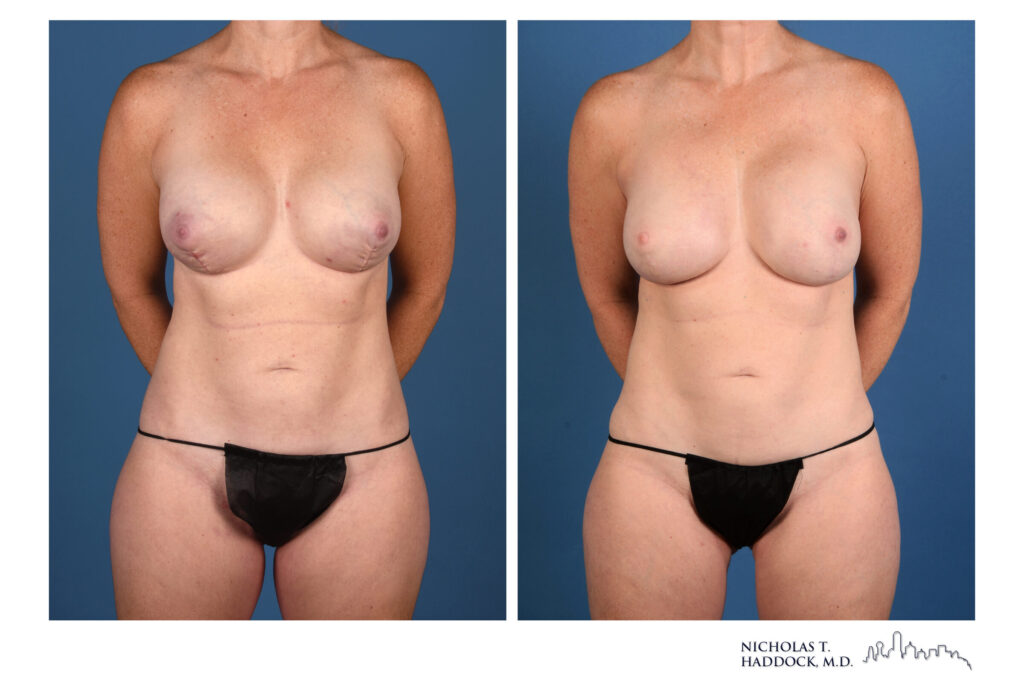
Individual results vary. Dr. Haddock posts a range of results to give patients a broad range of possible expectations. A large portion of the differences amongst results is a result of the patient anatomy and/or previous treatments. Photos are shared with each patient’s permission.
In microsurgery, experience is the variable that determines the result. Our practice holds the largest published LAP flap series in the world.†
Choosing your surgeon
The LAP flap is a new and technically demanding operation, and Dr. Haddock and his team are one of only a few groups performing it anywhere in the world. They published the initial experience with simultaneous bilateral LAP flaps — doing both sides in one operation rather than one side at a time — and, to our knowledge, remain the group with the most extensive experience doing it that way. Their 300-flap series is the largest report of LAP flaps in the medical literature.
Dr. Haddock’s approach is built around a few clear goals: superior aesthetic results, limited donor-site morbidity (fewer problems where the tissue is taken), and operative efficiency that leads to a quicker recovery. When you are choosing a surgeon for this operation, experience is the thing that matters most — and Dr. Haddock does not view success as simply flap survival; his goal is to achieve the result each patient wants.
What recovery looks like
Dr. Haddock typically performs these operations at William P. Clements Jr. University Hospital in Dallas, using an Enhanced Recovery After Surgery (ERAS) protocol designed for a faster recovery and less postoperative discomfort.
- A 3 to 5-night stay in the hospital, sometimes longer
- Extra nursing care to monitor blood flow to the flap — on a regular hospital floor, not in an ICU
- About 6 weeks of restricted activity
- Some tightness in the trunk — usually improving between 3 and 6 months
Printable instructions for your operation and your recovery:
- LAP flap instructionsPDF
- Drain carePDF
- Medications to avoidPDF
- Protein supplementationPDF
- Scar managementPDF
LAP flap, in more detail
Why is there also an incision on the lower abdomen?
This is the detail that makes a LAP flap different from the more common flaps. The blood vessels supplying tissue from the lower back travel close to the spine. To avoid dissecting near important nerves, those vessels are deliberately taken short — too short, on their own, to reach and be connected at the chest. So a short additional length of blood vessel is needed to bridge the distance. It most often comes from the lower abdomen, through a small separate incision similar to a C-section, though other sources can be used when needed. Those vessels are joined to the vessels of the back tissue, and the combined tissue is then transferred to recreate the breast.
Can both sides be done at once?
When reconstruction is bilateral, Dr. Haddock often performs both LAP flaps in the same operation — though whether that is the right plan for you is decided case by case, based on your anatomy and your medical history. Most other centers that offer the procedure do one side at a time. His team published the initial experience with simultaneous bilateral LAP flaps, and to our knowledge still has the most extensive experience with it — which, when it is the right choice, means one operation and one recovery instead of two.
How long does the surgery take?
One side can take 5 to 7 hours; both sides, 8 hours or more. The extra time comes from turning you over during the operation and from additional blood-vessel connections.
How many surgeries will I need?
Most patients have a second stage, a touch-up operation, to refine the cosmetic result and, if needed, to reconstruct the nipple.
Can I have a LAP flap if I have had, or will need, radiation?
Yes, but we prefer to do the LAP flap after radiation, not before. If you will need, or might need, radiation, we recommend a delayed-immediate approach with a tissue expander.
What is a LAP flap?
A LAP (lumbar artery perforator) flap is a natural-tissue (autologous) breast reconstruction that uses skin and fat from the love handle (flank) and lower back. It takes only skin and fat; all of the muscle is preserved. LAP flaps are more complex than other options, but in Dr. Haddock’s experience they often give one of the best cosmetic results in breast reconstruction.
Where is the scar, and how do the back and flanks look afterward?
The scar usually settles along the upper edge of the pelvic bone. Because the area just above the buttock is reduced, this often gives the illusion of a buttock lift. Lower-back swelling settles over the first few months, and any numbness there usually fades with time.
Does the LAP flap take any muscle?
No. It is a perforator flap: its blood vessel runs between two back muscles, and Dr. Haddock frees it from between them without taking muscle.
Who is a LAP flap for?
The lower back is an alternative option for breast reconstruction. The LAP flap is typically considered when the abdomen is not available, for example because of earlier surgery or an earlier reconstruction there. The choice between the thighs and the lower back is made individually for each patient.
What is recovery like (time off, sitting, lying on your back)?
Most patients stay in the hospital for 3 to 5 nights while nurses closely watch the blood flow to the new breast. Walking is often encouraged while in the hospital and increased over the first two weeks. You can sit, but sitting fully upright puts tension on the closure and can be uncomfortable at first. Lying down and standing are typically comfortable, because they take all the tension off the closure. You should not lift anything heavier than 10 pounds or exercise for six weeks. There is no driving for about 10–14 days, and not until you’re off prescription pain medicine and muscle relaxers. Your reflexes must also be fast enough to be safe, and everyone is different in how quickly they get there. Some tightness in the trunk is normal and usually improves between three and six months.
In their words
“My experience was great with Dr. Haddock. His staff is so kind and his integrity and bedside manner is wonderful. Of course, the best part is the results.”
“I am a breast cancer survivor!! And I can truly say that when I look in the mirror I don’t see a daily reminder that I once had cancer that took away the old models of my breast because Dr. Haddock gave me new models that make me feel so good about myself!!”
Hear from patients
Patients describe their LAP flap reconstruction in their own words.
Potential complications
As with any procedure, there are risks associated with natural-tissue (autologous) breast reconstruction. The main adverse outcomes are total or partial flap failure. Total failure — the most feared complication — typically results from a venous or arterial clot in the vessels supplying the flap; with modern technique and in experienced hands, this risk is extremely low. Patients may also experience hematoma, seroma, or wound-healing problems at either the donor or recipient site.
In Dr. Haddock’s series of 300 LAP flaps, the complication rate for non-stacked reconstructions (one flap per breast) fell from 30.2% in 2019 to 8.8% in 2024–25 as the technique was refined — the kind of improvement that only shows up when one team performs the operation often enough to study it.†
Videos, articles & resources
Medically reviewed by Dr. Nicholas Haddock, October 2026.
Considering LAP flap reconstruction?
Tell us a little about yourself and Dr. Haddock’s office will reach out to help you schedule a consultation.
Request a Consultation